

Painful periods that keep you home from work, pain during sex, bloating, and months of being told it is “normal”: for many women this is the road to an endometriosis diagnosis, often several years after the first symptoms. This guide explains what the condition is, how it is diagnosed, how treatment for endometriosis is stepped up from tablets to surgery, and how fertility fits into the plan.
What endometriosis is
The endometrium is the lining of the uterus that builds up and sheds each month. In endometriosis, tissue similar to this lining grows outside the uterus, most commonly on the ovaries, the ligaments behind the uterus, the peritoneum (the lining of the pelvis), the bowel surface and the bladder. This tissue also responds to monthly hormones, so it bleeds with no way out, causing inflammation, scarring, adhesions (organs sticking together) and ovarian cysts filled with old blood (endometriomas, or “chocolate cysts”).
It affects roughly 1 in 10 women of reproductive age. It is not an infection, not caused by anything the woman did, and not cancer, though it is chronic and needs long-term management.
Symptoms that should prompt a check
- Period pain that is severe, worsening over the years, or not relieved by ordinary painkillers
- Pelvic pain between periods
- Deep pain during or after intercourse
- Painful bowel movements or urination, especially around the period
- Heavy or irregular bleeding
- Difficulty conceiving after a year of trying (six months if over 35)
- Fatigue, bloating (“endo belly”), nausea around periods
Pain severity does not match the extent of disease; some women with small deposits have disabling pain while others with large cysts have few complaints. A gynaecologist consultation for endometriosis symptoms, irregular periods or PCOS is the right starting point when any of the above has gone on for more than two or three cycles.
How it is diagnosed
- History and examination: a pelvic examination may find tenderness or nodules.
- Transvaginal ultrasound: picks up endometriomas and some deep disease; it cannot see small peritoneal deposits, so a normal scan does not rule the condition out.
- MRI pelvis: used for deep infiltrating disease involving bowel, bladder or the recto-vaginal space, and for surgical planning.
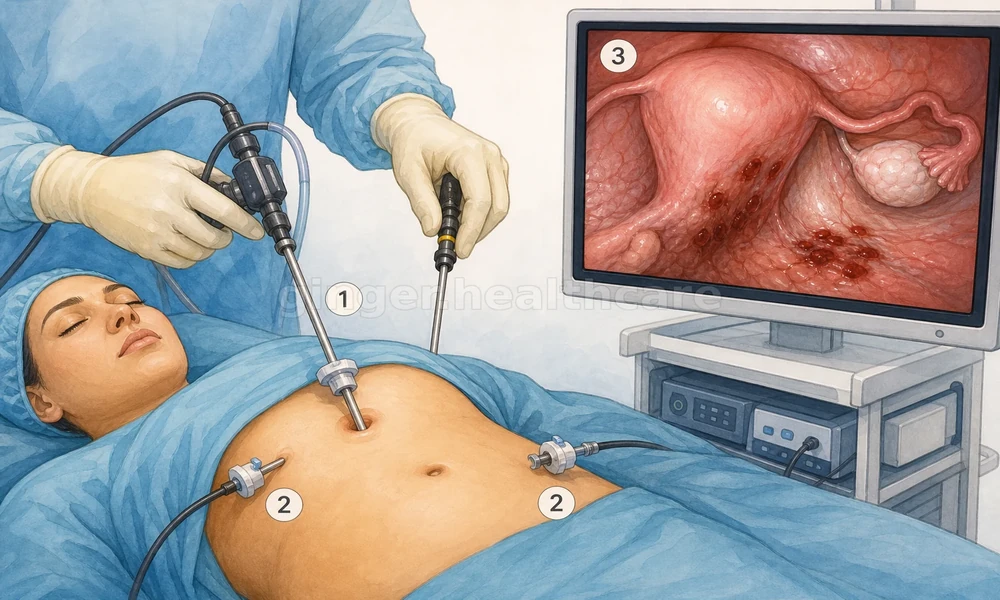
- Laparoscopy: keyhole surgery under general anaesthesia that allows the surgeon to see and remove the tissue. It remains the definitive test, but current guidelines allow treatment to start on the basis of symptoms and imaging without waiting for surgery.
CA-125 blood tests are sometimes raised but are not reliable for diagnosis.
The treatment ladder
The approach depends on three things: how bad the pain is, whether you want to conceive now or later, and what the scans show.
Step 1: pain relief and lifestyle. NSAIDs such as mefenamic acid or naproxen started a day before the period, heat, regular exercise and sleep hygiene. Pelvic-floor physiotherapy helps some women.
Step 2: hormonal therapy. The aim is to stop the monthly hormonal stimulation of the deposits.
- Combined oral contraceptive pills, taken continuously to skip periods
- Progestogen-only options: dienogest tablets, norethisterone, the levonorgestrel intrauterine system (hormonal IUD) or depot injections
- GnRH agonists or antagonists, which create a temporary menopause-like state; usually limited to 6 months, with “add-back” therapy to protect bone
- Aromatase inhibitors in selected resistant cases
Hormonal treatment controls symptoms but does not remove the tissue, so pain may return when it is stopped. It is also contraceptive, so it is not used when pregnancy is being attempted.
Step 3: laparoscopic surgery. Keyhole surgery to excise or burn (ablate) deposits, remove endometriomas while preserving healthy ovary, and divide adhesions. Reasons to operate include pain not controlled by medicines, an endometrioma larger than 3-4 cm, deep disease affecting bowel or bladder, and infertility where surgery may improve the chance of natural conception. Recovery is usually 1-2 weeks. Deciding between ovarian cyst monitoring or laparoscopic surgery depends on cyst size, symptoms and fertility plans.
Step 4: hysterectomy, with or without removal of the ovaries. Considered only when the family is complete, other options have failed, and the woman understands that pain may persist if deposits remain elsewhere.
Fertility considerations
Endometriosis can reduce fertility through blocked tubes, adhesions, poorer egg quality and inflammation, yet many women conceive naturally or with help. Points worth discussing early:
- If pregnancy is wanted soon, hormonal suppression is skipped and the choice is between trying naturally for a set period, laparoscopy, or assisted reproduction (IUI or IVF).
- Repeated surgery on the ovaries can reduce egg reserve; an AMH test before surgery helps planning.
- Egg freezing may be discussed for women with severe disease who are not ready for pregnancy.
- Pregnancy itself often eases symptoms temporarily but is not a treatment.
Indicative costs in India
Approximate ranges: a specialist consultation with ultrasound INR 1,500-4,000; hormonal medicines INR 500-3,000 per month depending on the option; laparoscopic excision INR 80,000-2 lakh in private hospitals, varying with city, hospital, extent of disease and insurance cover. The exact estimate comes from the treating gynaecologist. Most insurance plans cover laparoscopy for endometriosis after the waiting period.
Living with endometriosis
Because it is chronic, a long-term plan matters more than any single procedure. Keep a symptom diary, continue hormonal therapy after surgery to delay recurrence, review annually, and seek support for the emotional load, which is real and often under-acknowledged. The gynaecology and obstetrics department at a multispeciality hospital can coordinate pain management, surgery and fertility care under one roof.
When to seek urgent care
Sudden severe pelvic pain with vomiting or fainting may indicate a ruptured or twisted ovarian cyst and needs an emergency visit. Heavy bleeding with dizziness also needs same-day care.
The right treatment for endometriosis is the one matched to your pain, your scan findings and your family plans, reviewed as those change over the years.
Disclaimer: This article is for general information only and is not a substitute for medical advice. Please consult a qualified gynaecologist for the diagnosis and treatment of endometriosis.






